Fractures
of the Radius and Ulna
Fractures of the head of the radius
can occur from falls on the outstretched hand. As the force is transmitted along the radius,
can occur from falls on the outstretched hand. As the force is transmitted along the radius,
the head of the radius is driven sharply against the
capitulum, splitting or splintering the head
.
.
Fractures of the neck of the radius
occur in young children from falls on the outstretched hand.
occur in young children from falls on the outstretched hand.
Fractures of the shafts of the radius
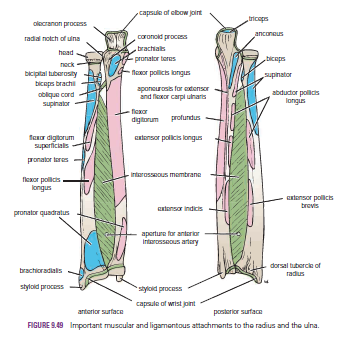
and ulna may or may not occur together. Displacement of the fragments is usually considerable and depends on the pull of the attached muscles. The proximal fragment of the radius is supinated by the supinator and the biceps brachii muscles. The distal fragment of the radius is pronated and pulled medially by the pronator quadratus muscle. The strength of the brachioradialis and extensor carpi radialis longus and brevis shortens and angulates the forearm. In fractures of the ulna, the ulna angulates posteriorly. To restore the normal movements of pronation and supination, the normal anatomic relationship of the radius, ulna, and interosseous membrane must be regained.
and ulna may or may not occur together. Displacement of the fragments is usually considerable and depends on the pull of the attached muscles. The proximal fragment of the radius is supinated by the supinator and the biceps brachii muscles. The distal fragment of the radius is pronated and pulled medially by the pronator quadratus muscle. The strength of the brachioradialis and extensor carpi radialis longus and brevis shortens and angulates the forearm. In fractures of the ulna, the ulna angulates posteriorly. To restore the normal movements of pronation and supination, the normal anatomic relationship of the radius, ulna, and interosseous membrane must be regained.
A fracture of one forearm bone may be associated with a
dislocation of the other bone. In Monteggia’s fracture, for example, the shaft
of the ulna is fractured by a force applied from behind.
There is a bowing forward of the ulnar shaft and an anterior
dislocation of the radial head with rupture of the anular ligament. In Galeazzi’s
fracture, the proximal third of the radius is fractured and the distal end of
the ulna is dislocated at the distal radioulnar joint.
Fractures of the olecranon process
can result from a fall on the flexed elbow or from a direct
blow. Depending on the location of the fracture line, the bony fragment may be
displaced by the pull of the triceps muscle, which is inserted on the olecranon
process. Avulsion fractures of part of the olecranon process can be produced by
the pull of the triceps muscle. Good functional return after any of these
fractures depends on the accurate anatomic reduction of the fragment.
Colles’ fracture is a fracture of the distal end of the
radius resulting from a fall on the outstretched hand. It commonly occurs in
patients older than 50 years. The force drives the distal fragment posteriorly
and superiorly, and the distal articular
surface is inclined posteriorly. This posterior displacement
produces a posterior bump, sometimes referred to as the “dinner-fork deformity”
because the forearm and wrist resemble the shape of that eating utensil.
Failure to restore the distal articular surface to its normal position will
severely limit the range of flexion of the wrist joint.
Smith’s fracture is a fracture of the distal end of the
radius and occurs from a fall on the back of the hand. It is a reversed Colles’
fracture because the distal fragment is displaced anteriorly
Olecranon
Bursitis
A small subcutaneous bursa is present over the olecranon
process of the ulna, and repeated trauma often produces chronic bursitis.
The
Metacarpals and Phalanges
There are five metacarpal bones, each of which has a base, a
shaft, and a head
The first metacarpal bone of the thumb is the shortest and most mobile. It does not lie in the same plane as the others but occupies a more anterior position. It is also rotated medially through a right angle so that its extensor surface is directed laterally and not backward.
The first metacarpal bone of the thumb is the shortest and most mobile. It does not lie in the same plane as the others but occupies a more anterior position. It is also rotated medially through a right angle so that its extensor surface is directed laterally and not backward.
The bases of the metacarpal bones articulate with the distal
row of the carpal bones; the heads, which form the knuckles, articulate with
the proximal phalanges.
The shaft of each metacarpal bone is slightly concave forward and is triangular in transverse section. Its surfaces are posterior, lateral, and medial.
The shaft of each metacarpal bone is slightly concave forward and is triangular in transverse section. Its surfaces are posterior, lateral, and medial.
There are three phalanges for each of the fingers but only
two for the thumb.